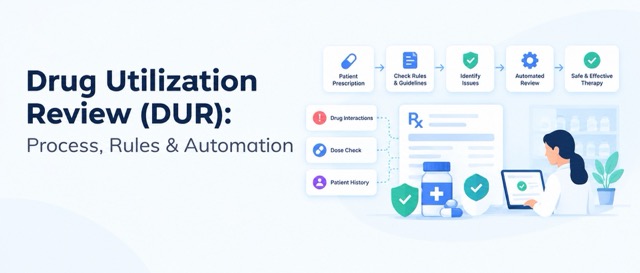
Prior authorization (PA) is a core workflow in pharmacy benefit management (PBM). It involves collecting member and prescription data, checking benefit and clinical criteria, requesting supporting documentation, routing exceptions for review, communicating decisions, and maintaining an audit trail.
Many PBMs still handle parts of this process through portals, faxes, phone calls, spreadsheets, and manual review queues. This makes PA harder to standardize, update, and scale.
Modern PA software can automate electronic intake, clinical-data collection, rules-based decisioning, documentation requests, reviewer routing, renewals, appeals, and audit tracking. However, these products do not solve the same problem. Some are built specifically for pharmacy-benefit PA, some focus on provider-PBM connectivity, and others provide clinical review or configurable rules and workflow automation.
This guide compares 8 PBM prior authorization software and solutions in 2026, focusing on their core capabilities, use cases, strengths, limitations, and where each fits in a PBM technology stack.
How We Picked These Tools
The comparison focuses on the technical and operational capabilities that determine how a prior authorization platform fits into a PBM workflow.
- PA intake and connectivity: We evaluated how each platform receives authorization requests and connects with providers, PBMs, pharmacies, and existing healthcare systems, including APIs, portals, EHR integrations, and other electronic workflows.
- Rules and decisioning: We considered how platforms represent and execute clinical, benefit, and coverage rules, including configurable decision logic, rule versioning, and support for changing policies without extensive engineering work.
- Clinical data and documentation: We looked at how each solution collects clinical information, retrieves supporting data, identifies missing documentation, and handles requests that require additional review.
- Workflow and exception management: We evaluated capabilities for routing cases to reviewers, managing exceptions, renewals, appeals, and other steps that cannot be fully automated.
- Integration and interoperability: We considered support for APIs and healthcare interoperability standards, along with how easily the platform can work alongside existing PBM, claims, pharmacy, and clinical systems.
- Auditability and reporting: We evaluated audit trails, decision history, reporting, and visibility into authorization status, since PBMs need to track how and why decisions were made.
- Pricing and deployment model: Where pricing is publicly available, we considered it directly. For vendors using quote-based pricing, we considered factors such as transaction volume, integrations, implementation requirements, and enterprise deployment.
Also Read: Rule Engine for Healthcare: Transforming Medical Decision-Making
The List, at a Glance
CoverMyMeds
CoverMyMeds is primarily an electronic prior authorization and healthcare connectivity platform. Its payer and PBM offering connects providers with health plans and PBMs, allowing PA requests to be initiated from existing provider workflows rather than separate payer portals.
Its main value sits at the ePA connectivity and submission layer, rather than as a PBM's internal clinical decision engine. CoverMyMeds says its network reaches 1M+ prescribers across 350+ EHRs, alongside pharmacy and payer connectivity.
Best for:
PBMs and health plans prioritizing provider connectivity and electronic PA adoption.
Key Features:
- ePA network: Routes PA transactions between connected providers, payers, PBMs, and pharmacies.
- EHR-embedded PA: Lets providers initiate PA from connected clinical workflows.
- Policy-mapped submissions: Surfaces plan-specific coverage rules, PA requirements, formulary, step therapy, and documentation requirements.
- Medical and pharmacy PA: Supports workflows across both medical and pharmacy benefits.
Pros:
- Large connectivity footprint: Reduces the need for PBMs to build individual provider connections.
- Strong provider integration: Brings PA into existing EHR workflows.
- Strong upstream PA layer: Particularly useful for intake and electronic transaction exchange.
Cons:
- Not a standalone decision engine: Complex internal benefit and clinical rules may require separate infrastructure.
- Network-dependent: Its value is closely tied to its connected provider and payer ecosystem.
- Limited control over core policy logic: Organizations wanting to own highly customized decision tables may need another layer.
Also Read: Automate Your Healthcare Business With Efficient BPM
Surescripts
Surescripts operates primarily as an e-prescribing and ePA network layer, connecting provider systems with PBMs and payers. Its ePA workflow delivers plan- and medication-specific questions to providers and returns the payer's determination within the prescribing workflow.
Technically, its strength is standardized transaction exchange. Its ePA implementation is based on the NCPDP SCRIPT standard and is designed specifically to move pharmacy-benefit PA information between provider vendors and PBM/payer systems.
Best for:
PBMs and health plans that need electronic PA embedded directly into prescribing workflows.
Key Features:
- Dynamic question sets: Sends plan- and drug-specific PA questions to the EHR.
- NCPDP SCRIPT connectivity: Supports standardized electronic PA messaging between provider and PBM/payer systems.
- Real-time benefit context: Uses eligibility and formulary information to determine when a PA request should be initiated.
- Electronic renewals: Supports renewal prompts as an authorization approaches expiration.
Pros:
- Strong e-prescribing position: PA occurs within the workflow where prescriptions are already created.
- Standardized PBM connectivity: Reduces the need for custom point-to-point PA integrations.
- Plan-specific transactions: Supports dynamic questions and responses instead of static PA forms.
Cons:
- Primarily a connectivity layer: It does not replace the PBM's underlying clinical decision engine.
- Pharmacy-benefit focused: Its core ePA model is tied to medication coverage rather than broad medical PA.
- Dependent on upstream data: Effective routing relies on accurate eligibility, formulary, and payer identification data.
Agadia PAHub
Agadia PAHub is a pharmacy-benefit-specific PA management platform built for health plans and PBMs. Unlike connectivity-first platforms, PAHub focuses on managing the authorization itself—from intake and criteria evaluation through decisioning and downstream communication.
Its architecture is therefore closer to the PBM's operational PA layer, with configurable workflows and automated adjudication rather than simply transporting PA transactions. Agadia reports 105M+ lives managed, 19M+ PAs processed annually, and an average 78% auto-adjudication rate.
Best for:
PBMs and health plans managing high-volume pharmacy-benefit PA operations.
Key Features:
- Pharmacy-benefit PA management: Purpose-built workflows for drug authorization under the pharmacy benefit.
- Automated adjudication: Evaluates eligible requests against configured PA criteria without requiring manual review for every case.
- Configurable workflows: Supports plan-specific criteria, routing, notices, and operational processes.
- PA lifecycle management: Handles electronic PA, decisions, documentation, and downstream workflow requirements.
Pros:
- PBM-specific architecture: Designed around pharmacy-benefit operations rather than generic workflow automation.
- High-volume automation: Built for large PA populations and automated decision processing.
- Established PA platform: Longstanding deployment across health plans and PBMs.
Cons:
- Pharmacy-benefit focused: Less suitable when the primary requirement spans broad medical-benefit authorization.
- Enterprise implementation: Its depth makes it more appropriate for organizations with established PBM infrastructure.
- Less general-purpose than a rules engine: Teams wanting to reuse the same decision layer outside PA may prefer a broader platform.
Also Read: How Decision Engines Reduce Service Errors
Banjo Health
Banjo Health is an AI-driven PA management and clinical decisioning platform designed for health plans and PBMs. Its key differentiator is converting clinical criteria into executable decision logic and applying that logic during PA review.
Rather than focusing primarily on network connectivity, Banjo sits closer to the PA intake, clinical review, decisioning, and appeals layer. Its platform supports both medical and pharmacy PA.
Best for:
Health plans and PBMs looking to automate clinical PA review while retaining clinician control.
Key Features:
- Clinical decision-tree generation: Converts complex clinical guidelines into electronic decision trees.
- AI-assisted review: Extracts case information and compares it against predefined clinical criteria.
- End-to-end PA workflow: Covers intake, case creation, clinical review, decisioning, and appeals.
- API-first architecture: Connects the PA workflow with existing systems and data sources.
Pros:
- Clinical criteria automation: Goes beyond simple request routing into clinical decision support.
- Human-controlled decisions: AI can recommend outcomes while clinical experts retain final decision authority.
- Medical + pharmacy coverage: Broader PA scope than pharmacy-only platforms.
Cons:
- AI governance required: Automated clinical recommendations still need appropriate review and controls.
- Not an ePA network: PBMs may still need separate connectivity infrastructure for provider-facing transactions.
- More specialized than a generic rules engine: Its value is strongest around PA-specific clinical workflows.
Nected
Nected occupies a different position from most products in this list. It is not a replacement for a PBM adjudication platform or an ePA network. Instead, Nected provides a configurable decisioning and workflow layer that can sit alongside existing PBM, claims, eligibility, PA, or data infrastructure.
For PBM use cases, Nected focuses on externalizing logic such as formulary tiers, exclusions, quantity limits, prior authorization criteria, step therapy, plan-level rules, and client-specific variations. Its architecture supports versioned rules, effective-dated rollouts, maker-checker approvals, historical-claims replay, shadow-mode testing, decision traces, and audit trails.
This distinction matters because PA logic that traditionally lives inside application code can instead be represented as configurable decision logic:
PA Request
    ↓
Member / Plan / Drug Data
    ↓
Clinical Criteria
    ↓
Decision Table / Rule Chain
    ↓
Approve / Reject / Review
    ↓
Workflow Action
Best for:
PBMs and healthcare technology teams that need configurable, versioned PA and benefit decisioning.
Key Features:
- Prior-auth and step-therapy logic: Represents clinical and benefit criteria as configurable decision rules.
- Decision tables and rule chains: Handles multi-condition PA and benefit logic without hard-coding every branch.
- Historical replay and shadow mode: Tests proposed rules against historical or live traffic before rollout.
- Rule governance and versioning: Supports approvals, effective dating, version control, rollback, and decision traces for controlled policy changes.
Pros:
- Policy logic is externalized: Benefit teams can change rules without tying every update to an application release.
- Strong governance: Version history, approvals, and decision traces make rule changes auditable.
- Reusable decision layer: The same architecture can support formulary, eligibility, adjudication, and other PBM decisions.
Cons:
- Not a PA network: It does not replace ePA connectivity platforms such as Surescripts.
- Not a complete PBM platform: Intake, provider communication, and other surrounding capabilities still need to come from the existing stack.
- Requires integration work: The PBM must provide the clinical, member, benefit, and prescription data needed by the rules.
Also Read: Rule Engine vs Workflow Engine: Key Differences
Myndshft
Myndshft is positioned as a unified medical and pharmacy PA automation platform, using generative AI, machine learning, and workflow automation across the PA lifecycle.
Its differentiator is breadth: rather than owning only connectivity or only decision logic, Myndshft combines requirement identification, initiation, submission, status management, and adjudication across medical and pharmacy PA.
Best for:
Healthcare organizations seeking a unified automation layer across medical and pharmacy PA.
Key Features:
- Unified medical + pharmacy PA: Supports both authorization types within one platform.
- Automated PA lifecycle: Covers requirement identification, initiation, submission, status, and adjudication.
- AI-driven workflow adaptation: Uses payer responses and workflow outcomes to update automated processes.
- Synchronized rules library: Maintains payer-specific rules across national, state, and regional plans.
Pros:
- Broad PA coverage: Avoids maintaining separate medical and pharmacy PA automation stacks.
- End-to-end workflow: Extends beyond decisioning into submission and status management.
- Adaptive automation: Its rules and workflows can respond to changing payer requirements.
Cons:
- Broader than PBM decisioning: Teams looking only to externalize benefit rules may not need its full workflow layer.
- AI-heavy architecture: Organizations may require additional governance around automated decisions and workflow changes.
- Less focused on a single PBM infrastructure layer: It spans multiple participants and PA workflows.
Infinx
Infinx approaches PA from a provider-side patient-access and revenue-cycle perspective rather than as a PBM's internal PA platform. Its Patient Access Plus platform uses AI agents to determine whether authorization is required, initiate requests, follow up with payers, and return authorization status to the provider's EMR.
This makes Infinx technically distinct from the PBM-first products in this list: its core problem is executing authorization operations across payer channels for healthcare providers, including cases where electronic submission is unavailable.
Best for:
Healthcare providers and pharmacy organizations that need automated PA operations across multiple payer channels.
Key Features:
- Authorization determination agent: Determines whether a service requires PA using payer guidelines and procedure data.
- Submission and follow-up agents: Initiate electronic requests and repeatedly check payer status.
- Human-in-the-loop processing: Routes non-electronic or complex cases to staff or Infinx specialists.
- EMR integration: Uses API or HL7-based integrations to update authorization information in provider systems.
Pros:
- Operational automation: Automates the repetitive determination, submission, and follow-up work providers perform today.
- Handles non-electronic payers: Can fall back to manual processing when a payer does not support electronic submission.
- AI + human model: Keeps specialists available for cases automation cannot complete.
Cons:
- Provider-centric: It is not primarily a PBM-side PA administration or clinical decisioning platform.
- Operational rather than policy-owned: It executes payer workflows rather than owning the PBM's underlying benefit criteria.
- Broader RCM positioning: Organizations looking specifically for pharmacy-benefit decisioning may need a more specialized platform.
Epidaurus Health
Epidaurus Health focuses on AI-driven pharmacy-benefit PA, with its technology being integrated with RxLogic's pharmacy adjudication infrastructure. The important architectural distinction is that the PA decisioning is being brought closer to the pharmacy-benefit adjudication environment, rather than operating only as a standalone provider workflow.
The integration is designed to combine clinical AI with current evidence and client-specific benefit criteria, allowing independent PBMs to automate more of the pharmacy PA process.
Best for:
Independent PBMs looking to add AI-driven pharmacy-benefit PA decisioning to their adjudication infrastructure.
Key Features:
- Clinical AI decisioning: Applies clinical evidence alongside client-specific benefit criteria.
- Pharmacy-benefit focus: Targets medication authorization rather than general medical PA.
- Adjudication integration: Connects PA decisioning with RxLogic's pharmacy claims infrastructure.
- Evidence-based processing: Uses current clinical evidence as part of authorization evaluation.
Pros:
- Close to the PBM core: PA decisioning can operate alongside pharmacy adjudication rather than as an isolated workflow.
- Pharmacy-specific: Designed around medication benefit and authorization requirements.
- AI + benefit criteria: Combines clinical reasoning with the PBM's own coverage rules.
Cons:
- Narrower scope: Primarily addresses pharmacy-benefit PA rather than medical authorization.
- Integration-specific: Its current positioning is closely tied to the RxLogic adjudication environment.
- Less general-purpose: Organizations wanting a reusable decision engine across multiple PBM functions may need a broader rules platform.
How to Choose PBM Prior Authorization Software
The right PBM PA software depends on which layer you need to fix. Before comparing vendors, identify whether the problem is PA operations, provider connectivity, clinical automation, rules management, or integration with the PBM's core systems.
Here are the main options:
- Choose pharmacy-benefit PA software when the problem is PA operations. Look for drug-specific criteria, formulary rules, automated adjudication, renewals, provider communication, and PA case management. Agadia PAHub fits this model.
- Choose an ePA connectivity platform when the problem is provider-to-PBM communication. Look for EHR/e-prescribing integration, electronic submissions, plan-specific questions, and PA status exchange. Surescripts and CoverMyMeds fit this layer.
- Choose an AI-driven PA platform when the problem is manual clinical or document-heavy work. Look for automated data extraction, clinical criteria interpretation, submission, follow-ups, and exception handling. Banjo Health, Myndshft, Infinx, and Epidaurus address different parts of this problem.
- Choose a decisioning layer when the problem is changing business rules. This is relevant when PA, formulary, step-therapy, or quantity-limit logic is buried in application code. Nected fits this architecture by externalizing rules and adding testing, approvals, versioning, and decision traces.
- Choose an integrated PBM architecture when PA depends directly on adjudication data. This matters when decisions require member eligibility, plan configuration, formulary data, claims history, and authorization history. Epidaurus with RxLogic represents this model.
PBM Prior Authorization Software vs. Traditional PA Workflows
PBM PA software replaces fragmented fax, phone, portal, and manual-review processes with connected electronic workflows for prescription authorization. Here is how the two approaches compare:
Bottom Line
There is no single best PBM prior authorization platform because these products operate at different layers of the PA stack. CoverMyMeds and Surescripts are strongest for electronic connectivity, while Agadia focuses on pharmacy-benefit PA management. Banjo Health and Myndshft target AI-driven PA automation, and Infinx focuses on provider-side authorization operations. Epidaurus targets AI-powered pharmacy PA alongside adjudication infrastructure.
Nected is different: it provides a configurable decisioning layer for PA, formulary, step-therapy, and benefit rules. The right choice depends on the specific architectural gap the PBM needs to solve.
FAQs
What is PBM prior authorization software?
PBM prior authorization software automates parts of the process used to determine whether a prescription meets a plan's benefit and clinical criteria. Depending on the platform, it can handle intake, data collection, decisioning, provider communication, and audit tracking.
What is the difference between PBM PA and medical PA?
PBM or pharmacy-benefit PA primarily covers prescription drugs and can involve formulary rules, step therapy, quantity limits, and drug-specific criteria. Medical PA generally covers services such as procedures, imaging, equipment, and other medical-benefit services.
Can PBM prior authorization be automated?
Yes. Software can automate PA identification, data collection, criteria matching, submission, status tracking, and routing. Complex or ambiguous cases can still require human clinical review.
How does ePA work for PBMs?
ePA replaces manual fax and phone workflows with electronic exchange between provider systems, EHRs, e-prescribing platforms, payers, and PBMs. The workflow can transmit plan-specific questions, clinical information, documentation, and authorization decisions electronically.
Can PA software integrate with PBM claims systems?
Yes. Integration can connect PA with eligibility, formulary, claims, and adjudication systems. The architecture varies by product: some platforms provide connectivity, while others operate as decisioning or PA-management layers alongside existing infrastructure.
What should PBMs look for in PA software?
Look for pharmacy-benefit PA support, configurable decisioning, ePA connectivity, EHR/API integration, claims and adjudication integration, human-in-the-loop workflows, rule versioning, audit trails, and the ability to test policy changes before production.